
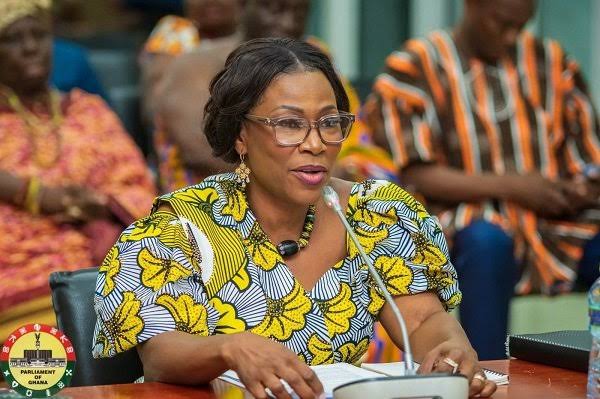
On 19 October, before Parliament’s Public Accounts Committee, Ghana’s Deputy Health Minister Dr Grace Ayensu-Danquah delivered a warning that cuts to the core of the country’s public health governance: without a dedicated domestic budget line for maternal healthcare, Ghana will fail to meet its 2030 Sustainable Development Goal targets on maternal mortality. The statement was not rhetorical. It named a structural financing failure that has persisted across successive administrations and that now, with less than six years to the SDG deadline, carries measurable consequences for Ghanaian women and for the country’s credibility within continental health governance frameworks.
Ghana’s maternal mortality ratio remains a persistent governance concern. The country recorded approximately 310 maternal deaths per 100,000 live births in recent years, a figure that places it well above the SDG 3.1 target of fewer than 70 per 100,000 by 2030. Across ECOWAS, the picture is similarly uneven: Senegal has made measurable gains through community health worker integration, while Nigeria’s federal health financing fragmentation continues to suppress outcomes in its northern states. Ghana, positioned between these two realities, has the institutional capacity to lead on maternal health reform but has not yet aligned its fiscal architecture to match that ambition.
Dr Ayensu-Danquah’s appeal to the Public Accounts Committee was precise in its institutional logic. She requested a dedicated line item in the national budget for maternal health services, arguing that without ring-fenced domestic funding, the sector remains hostage to donor cycles, supplementary budget negotiations, and the discretionary priorities of successive finance ministries. “It is only when we have sustainable funding that is domestically funded that we can solve this problem,” she told the committee. “Otherwise, by 2030, we won’t meet any of these criteria.” That framing matters: it shifts the conversation from humanitarian appeal to fiscal accountability, from charity to governance obligation.
The clinical dimension of her testimony reinforces the urgency of the governance argument. Dr Ayensu-Danquah identified haemorrhage as the leading cause of maternal deaths in Ghana, a finding consistent with WHO data across sub-Saharan Africa where postpartum haemorrhage accounts for roughly one-third of maternal fatalities. She drew a direct line between anaemia, which is detectable and manageable at the primary healthcare level, and the severity of blood loss during delivery. When anaemia goes undetected in the antenatal period, it becomes a life-threatening condition at the moment of childbirth. This is not a clinical mystery. It is a systems failure, one rooted in underfunded community health infrastructure and inadequate supply chains for iron supplementation and diagnostic tools.
The financing architecture for Ghana’s health sector reflects a broader vulnerability shared across West Africa. A significant portion of health expenditure in the region remains externally sourced, leaving national health systems exposed to shifts in donor priorities, currency fluctuations, and geopolitical recalibrations in development finance. Ghana’s National Health Insurance Scheme, once a model for domestic health financing innovation in the region, has faced recurring liquidity crises that have strained provider reimbursements and eroded service quality. Against this backdrop, the Deputy Minister’s call for a maternal health budget line is not an incremental request; it is a structural correction to a financing model that has consistently failed to protect women at their most vulnerable.
Within the ECOWAS regional integration framework, maternal health financing carries implications beyond national borders. The ECOWAS Health Policy adopted by member states commits signatories to harmonized health systems strengthening, and the African Union’s Agenda 2063 explicitly links human capital development to continental economic transformation. When a member state like Ghana signals that it cannot domestically fund a core component of primary healthcare without parliamentary intervention, it exposes a gap between regional policy commitments and the fiscal realities that underpin them. Ivory Coast, which has invested more consistently in community health infrastructure in recent years, offers a partial regional benchmark, though its own maternal mortality indicators remain above SDG thresholds.
For investors and development finance institutions operating in Ghana, the maternal health financing debate is also a governance signal. A state’s capacity to fund preventive and primary healthcare domestically is a proxy indicator for institutional reliability, long-term human capital formation, and the sustainability of social contracts that underpin political stability. The AfCFTA framework, which envisions a continental market of over 1.4 billion people, depends on productive, healthy populations. Ghana’s role as one of AfCFTA’s early institutional champions makes its domestic health financing choices a matter of regional strategic interest, not merely domestic social policy.
The Public Accounts Committee now holds a concrete institutional decision. Approving a dedicated maternal health budget line would establish a precedent for ring-fenced social expenditure within Ghana’s fiscal framework, a reform that health economists and governance analysts have long advocated as a mechanism for insulating essential services from annual budget volatility. It would also send a signal to ECOWAS peers and to international health financing bodies, including Gavi and the Global Fund, that Ghana is committed to co-financing arrangements rather than passive dependency. The alternative, continuing to absorb maternal health expenditure into broad health sector allocations subject to discretionary cuts, has already demonstrated its inadequacy across multiple budget cycles. Dr Ayensu-Danquah’s testimony named the problem with institutional precision. The response now belongs to Parliament.



